
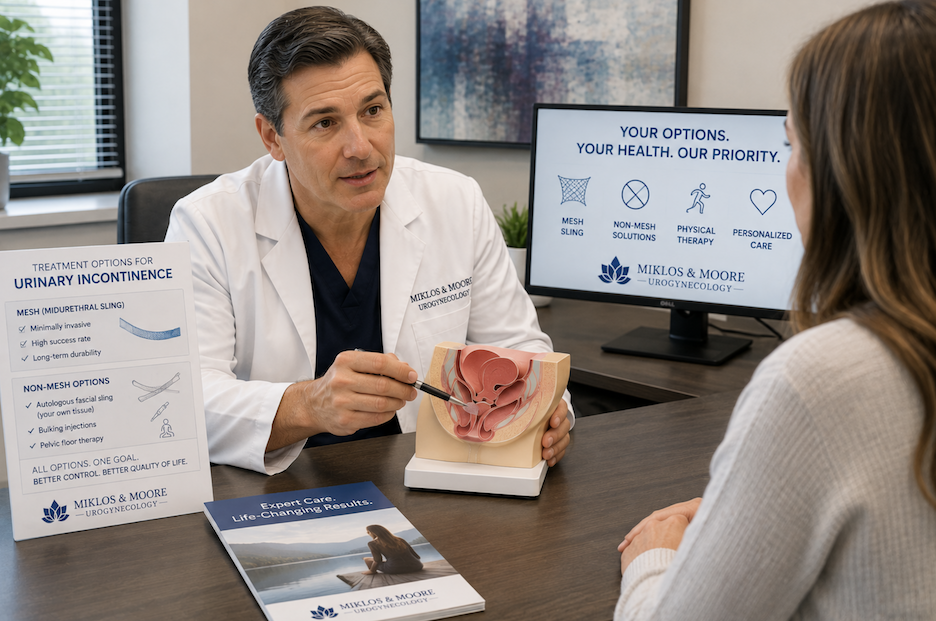
Do I Need Mesh for Urinary Incontinence? Understanding Mesh and Non-Mesh Treatment Options
Learning that you may need surgery for urinary incontinence can feel overwhelming. One of the first questions many women ask is:
“Will I need mesh?”
For years, news reports and advertisements have created confusion about surgical mesh. While some stories have highlighted serious complications associated with certain types of pelvic mesh, they have also caused many women to avoid treatments that may actually be safe and highly effective for their specific condition.
The reality is far more nuanced.
Not all mesh procedures are the same, and not every woman with urinary incontinence requires mesh. In fact, there are both mesh and non-mesh treatment options available, and the best choice depends on your symptoms, anatomy, medical history, and personal preferences.
Understanding your options allows you to make an informed decision with your physician rather than relying on headlines or misinformation.
What Is Stress Urinary Incontinence?
Stress urinary incontinence (SUI) occurs when physical activity places pressure on the bladder, causing urine leakage.
Women commonly leak urine when they:
- Cough
- Sneeze
- Laugh
- Exercise
- Run
- Lift heavy objects
- Jump
- Change positions quickly
Stress urinary incontinence is extremely common, especially after pregnancy, childbirth, menopause, and aging.
It is not a normal part of aging, and effective treatments are available.
Why Does Urinary Incontinence Happen?
The bladder and urethra rely on strong muscles, ligaments, and connective tissues for support.
When these support structures weaken, urine may leak during activities that increase abdominal pressure.
Several factors increase the risk of stress urinary incontinence:
- Pregnancy
- Vaginal childbirth
- Menopause
- Aging
- Obesity
- Chronic coughing
- Heavy lifting
- Previous pelvic surgery
- Genetics
The severity of leakage varies from occasional drops to larger amounts that interfere with daily life.
What Is Surgical Mesh?
Surgical mesh is a synthetic material designed to provide additional support to weakened tissues.
For stress urinary incontinence, the most common mesh procedure is the midurethral sling.
During this procedure, a narrow strip of mesh is placed beneath the urethra to provide support when pressure increases during coughing, laughing, or exercise.
The mesh acts like a hammock, helping the urethra remain closed during physical activity.
Midurethral slings have been used for many years and are supported by extensive clinical research for appropriately selected patients.
It is important to understand that the mesh used for stress urinary incontinence is different from larger mesh products that were previously used for certain pelvic organ prolapse repairs and later removed from the U.S. market.
Are Mesh Slings Safe?
For many women, yes.
When performed by experienced surgeons on carefully selected patients, midurethral slings have demonstrated high success rates and long-term durability.
Like every surgical procedure, however, they also carry risks.
Potential complications include:
- Bleeding
- Infection
- Temporary difficulty emptying the bladder
- Mesh exposure
- Pelvic pain
- Urinary urgency
- Persistent leakage
- Need for additional treatment
Fortunately, serious complications are uncommon, particularly when surgery is performed by surgeons experienced in female pelvic reconstructive surgery.
The decision to use mesh should always involve a thorough discussion of benefits, risks, and available alternatives.
What Are Non-Mesh Options?
Not every woman requires mesh surgery.
Depending on the severity of your symptoms, treatment options may include:
- Pelvic floor physical therapy
- Kegel exercises
- Lifestyle modifications
- Weight loss
- Bladder training
- Vaginal pessaries
- Urethral bulking injections
- Behavioral therapy
Many women experience significant improvement without surgery.
What Is an Autologous Fascial Sling?
For women who prefer to avoid synthetic mesh, an autologous fascial sling may be an option.
Instead of using synthetic material, the surgeon creates a sling using a small strip of the patient’s own tissue, typically taken from the lower abdominal wall.
This procedure provides support beneath the urethra without permanent synthetic mesh.
Although recovery is generally somewhat longer than with a midurethral sling, it remains an effective option for selected patients.
What Are Urethral Bulking Injections?
Bulking injections offer another non-mesh treatment option.
During the procedure, a specialized material is injected around the urethra to improve closure and reduce leakage.
Benefits include:
- No synthetic mesh
- Outpatient treatment
- Minimal recovery time
- No abdominal incisions
Bulking injections often work best for women with mild to moderate stress urinary incontinence and may require repeat treatments over time.
How Do You Know Which Treatment Is Right?
There is no single treatment that is best for every woman.
Your physician will consider:
- Your symptoms
- Severity of leakage
- Pelvic examination findings
- Previous surgeries
- Lifestyle
- Activity level
- Medical history
- Personal preferences
- Future pregnancy plans
Choosing the right treatment is highly individualized.
Questions to Ask Your Surgeon
Before deciding on surgery, consider asking:
- Do I actually need surgery?
- Am I a candidate for non-surgical treatment?
- Why are you recommending mesh?
- What non-mesh alternatives are available?
- How many sling procedures have you performed?
- What complications have you encountered?
- What is the expected recovery?
- How successful is this procedure?
- What happens if the first treatment doesn’t work?
An experienced surgeon should encourage these discussions and help you understand every available option.
Why Choose Miklos & Moore Urogynecology
Choosing treatment for urinary incontinence is a highly personal decision, and every woman deserves clear information about both mesh and non-mesh options.
Dr. John Miklos and Dr. Robert Moore are fellowship-trained urogynecologists specializing in Female Pelvic Medicine and Reconstructive Surgery (FPMRS). Their practice focuses exclusively on diagnosing and treating pelvic floor disorders, including stress urinary incontinence, overactive bladder, pelvic organ prolapse, and complex reconstructive conditions.
Rather than recommending the same treatment for every patient, Drs. Miklos and Moore perform a comprehensive evaluation to determine the underlying cause of urinary leakage and develop a personalized treatment plan based on each woman’s symptoms, anatomy, lifestyle, and goals.
Whenever appropriate, conservative treatments such as pelvic floor physical therapy and behavioral modifications are considered before surgery. When surgery is recommended, patients receive detailed counseling regarding both mesh and non-mesh options, allowing them to make informed decisions based on the latest medical evidence and their individual preferences.
Their decades of experience and commitment to patient education have made Miklos & Moore Urogynecology a trusted destination for women seeking expert care for urinary incontinence.
Frequently Asked Questions
Does every woman with urinary incontinence need mesh surgery?
No. Many women improve with pelvic floor therapy, lifestyle changes, medications, pessaries, or bulking injections. Surgery is recommended only when appropriate.
Is all surgical mesh the same?
No. The mesh used in midurethral slings differs from the larger transvaginal mesh products previously used for some prolapse repairs. These are different procedures with different indications and safety data.
Can I choose a non-mesh procedure?
Yes. Depending on your condition, non-mesh treatments such as an autologous fascial sling or urethral bulking injections may be appropriate.
How successful are midurethral slings?
For appropriately selected patients, midurethral slings have demonstrated high long-term success rates in treating stress urinary incontinence.
Will surgery completely eliminate leakage?
Many women experience significant improvement, but results vary. Your surgeon will discuss realistic expectations based on your specific condition.
Can urinary incontinence come back after treatment?
Yes. Aging, future pregnancies, weight changes, or other pelvic floor conditions may contribute to recurrence over time.
Is recovery difficult?
Recovery depends on the procedure performed. Most women gradually return to normal activities over several weeks while following their surgeon’s postoperative instructions.
Will insurance cover urinary incontinence treatment?
Most medically necessary evaluations and treatments for stress urinary incontinence are covered by insurance, although benefits vary by plan.
Should I get a second opinion?
If you have concerns about mesh or surgery, obtaining a second opinion from a fellowship-trained urogynecologist is a reasonable way to better understand your options.
The Bottom Line
The decision to use mesh for urinary incontinence should never be based on fear or headlines alone.
Modern treatment includes both mesh and non-mesh options, and the right choice depends on your individual symptoms, anatomy, medical history, and treatment goals.
A fellowship-trained urogynecologist can explain the benefits and risks of every available option, answer your questions, and help you choose the treatment that best fits your needs.
With today’s advanced therapies, most women can significantly improve bladder control, regain confidence, and return to the activities they enjoy without constantly worrying about urinary leakage.